Bridging the Gap: Why Reproductive Psychiatry is Essential for Women’s Healthcare
When a patient walks into our office six weeks postpartum and tells us she has not slept properly since delivery, that she cries in the car, that her thoughts have begun to frighten her, we are…
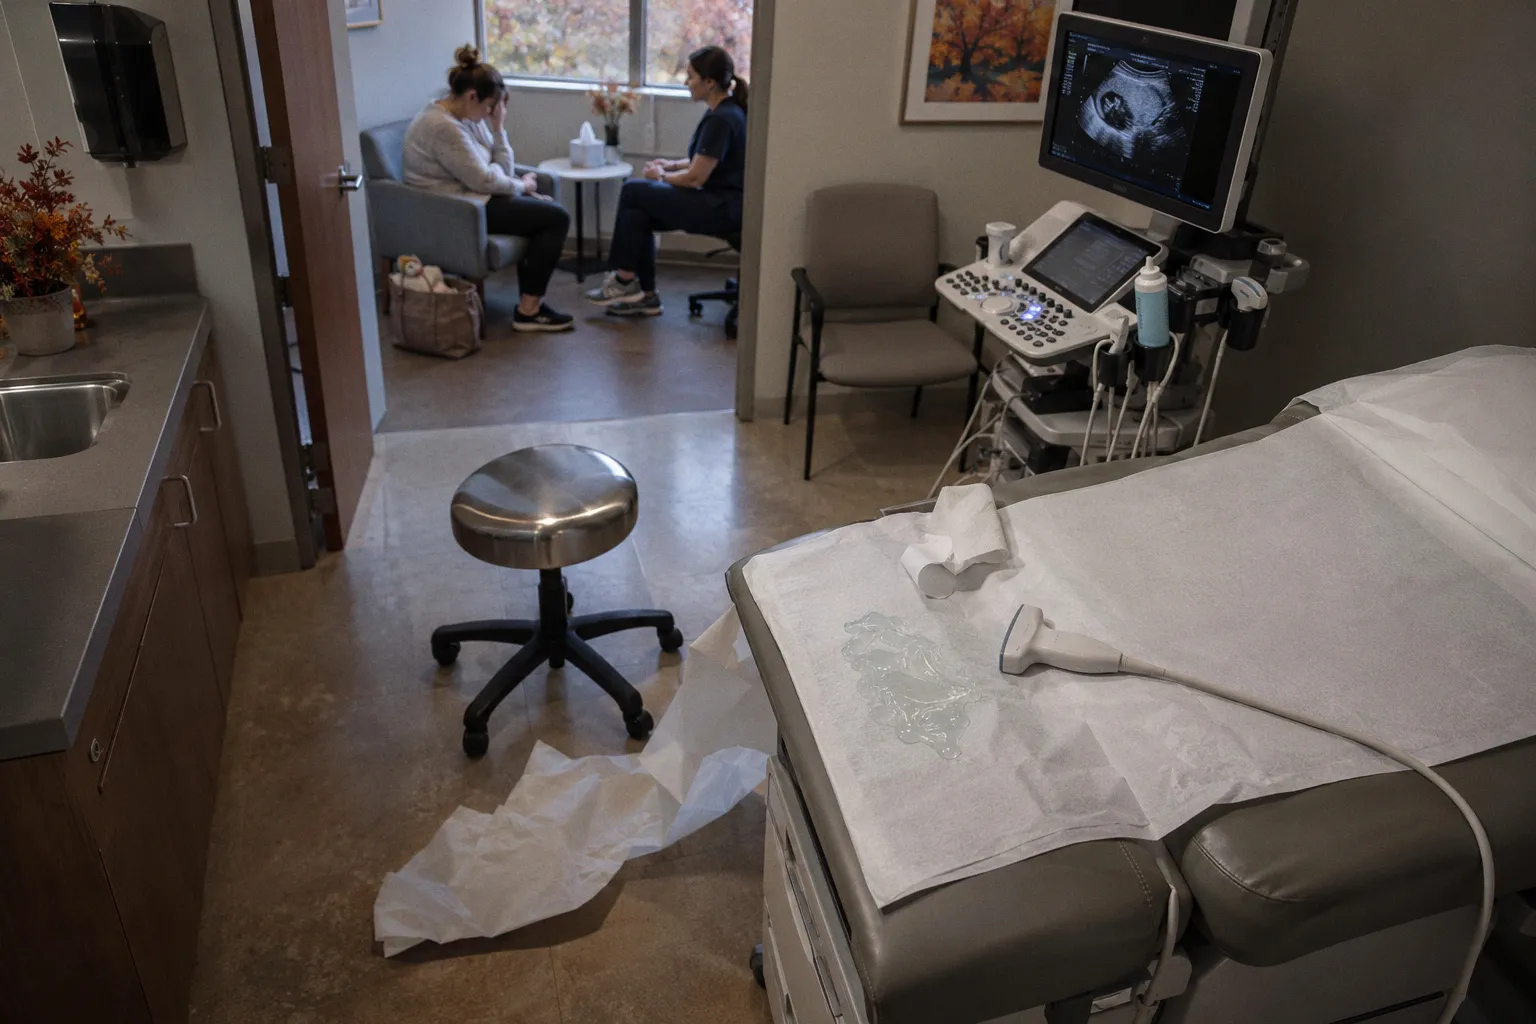
When a patient walks into our office six weeks postpartum and tells us she has not slept properly since delivery, that she cries in the car, that her thoughts have begun to frighten her, we are standing at a crossroads our training prepared us for, sort of, and then did not. A new essay on Nurse.org names this crossroads directly: the field that lives in between is called reproductive psychiatry, and women's health has been waiting a long time for it.
A field built for the hormonal seasons
Reproductive psychiatry is mental health care designed for the windows of life when hormones are quietly rewriting the brain's chemistry. As the Nurse.org piece outlines, that includes the months before conception, pregnancy, the first year after a baby arrives, the years of cycle-linked mood symptoms for those whose cycles carry a psychiatric load, and the long stretch of perimenopause and menopause.
What makes this a distinct specialty rather than a rebranding of general psychiatry is the recognition that the hormonal transition itself can be the driver. We often see patients whose anxiety was controlled for decades suddenly become relentless in their forties, or whose depression arrives without warning right as their cycles begin to shift. Treating those symptoms without naming the hormonal context underneath them tends to end in the same place the Nurse.org author kept finding in her own practice: patients being told, pointlessly, to simply wait it out.
Where the system keeps dropping patients
The piece draws on a midwife's career trajectory, from full-scope practice through menopause care, and the gap that kept appearing at the end of every referral list. The wait for a psychiatric appointment can run months. Many of the clinicians patients eventually reach are not comfortable treating someone who is pregnant or breastfeeding, and a parallel gap shows up for patients moving through perimenopause. Some patients are told to stop nursing, some are told to wait it out, and some simply stop calling back.
We recognize the same gap on the perimenopause side of the exam room, where mood changes are still routinely attributed to stress, to aging, or to a vague reassurance that it will pass on its own, when the underlying hormonal shift has a recognized treatment pathway. Recognizing the gap is the first step. Building the workforce to close it is the slower work, and it is the work patients feel every time they are asked to choose between being a credible psychiatric patient and being a credible hormonal one.
A next question worth bringing to your clinician
If any of this lands close to home, the most useful thing you can do at your next visit is to ask one specific question: whether your clinician collaborates with, or can refer you to, someone trained in reproductive psychiatry. In pregnancy and postpartum that matters because the medication question shifts across trimesters and across feeding plans, and a generalist may not feel equipped to navigate that. In perimenopause and menopause it matters because the hormonal transition can itself be driving the mood picture, and treating the brain without treating the hormones underneath tends to fall short.
You do not need to arrive with a diagnosis. You arrive with a timeline, your symptoms mapped against it, and a single request: that the hormonal context be part of the conversation from the beginning.